
Tag: breast implants consultation

  • Three Starting Points for a Breast Implant Consultation in Beverly Hills

    Three Starting Points for a Breast Implant Consultation in Beverly Hills

    Anatomy Sets the Frame for a Breast Implant Consultation

    A breast implant consultation in Beverly Hills can begin with what a person sees rather than with a number: a narrow breast base that still feels as though it needs fullness, a visible difference between the breasts, or limited upper-pole coverage paired with a preference for a softer transition. Each starting point changes what “more volume” needs to mean.

    Planning can consider skin and soft tissue, breast and chest-wall dimensions, breast shape, and the patient’s goals. Measurements establish planning boundaries rather than supplying a single answer. The visible feature a person wants to discuss gives those boundaries a purpose. A research review reported that tissue-based planning appeared preferable to approaches led primarily by preference, while also noting that further study was needed to clarify effects on outcomes.

    This feature follows three visible starting points through the planning conversation. In each, a desired amount of fullness remains relevant, but volume alone does not predict bra cup size, implant width, forward projection, or how an implant may appear on a particular body. Two implants with the same volume may have different widths and projection, and the same volume can appear differently with different breast width, chest-wall shape, tissue coverage, and profile.

    The Factors Behind the Conversation

    The same request for fullness can describe different visual concerns. One person may be focused on how far the breast projects forward, another on a difference from side to side, and another on the transition from chest to upper breast. The consultation has to distinguish those observations before treating them as one implant-sizing question.

    That distinction brings several features into view: breast-base width, tissue thickness, skin envelope, nipple level, lower-pole tissue, breast-fold support, and chest-wall symmetry. The skin envelope has its own degree of tightness or laxity, and the breast base sits on a chest wall with its own curvature and side-to-side differences. Skin excess or droop may be relevant because a volume concern and a positional concern are not necessarily the same concern. More significant droop may bring a lift into the discussion rather than being treated as an implant-size issue alone.

    These features are not a scorecard and do not supply a personal recommendation. They help separate the part of an appearance concern that relates to volume from the parts that may relate to position, coverage, shape, or the underlying chest wall.

    From a visible starting point to the features discussed

    “I want fullness without more width” → breast base width + profile + projection
    “One side looks different” → volume + shape + nipple level + chest-wall differences
    “I want a softer upper transition” → tissue coverage + dimensions + placement
    Skin envelope + nipple-to-fold relationship → position and shape considerations

    Nipple level in relation to the breast fold is a material measurement for implant-position planning. Existing lower-pole tissue and skin, implant characteristics, tissue compliance, and fold support may also be relevant to breast shape and implant position. The map does not turn an observation into a diagnosis; it shows why similar requests for volume can lead to different planning discussions.
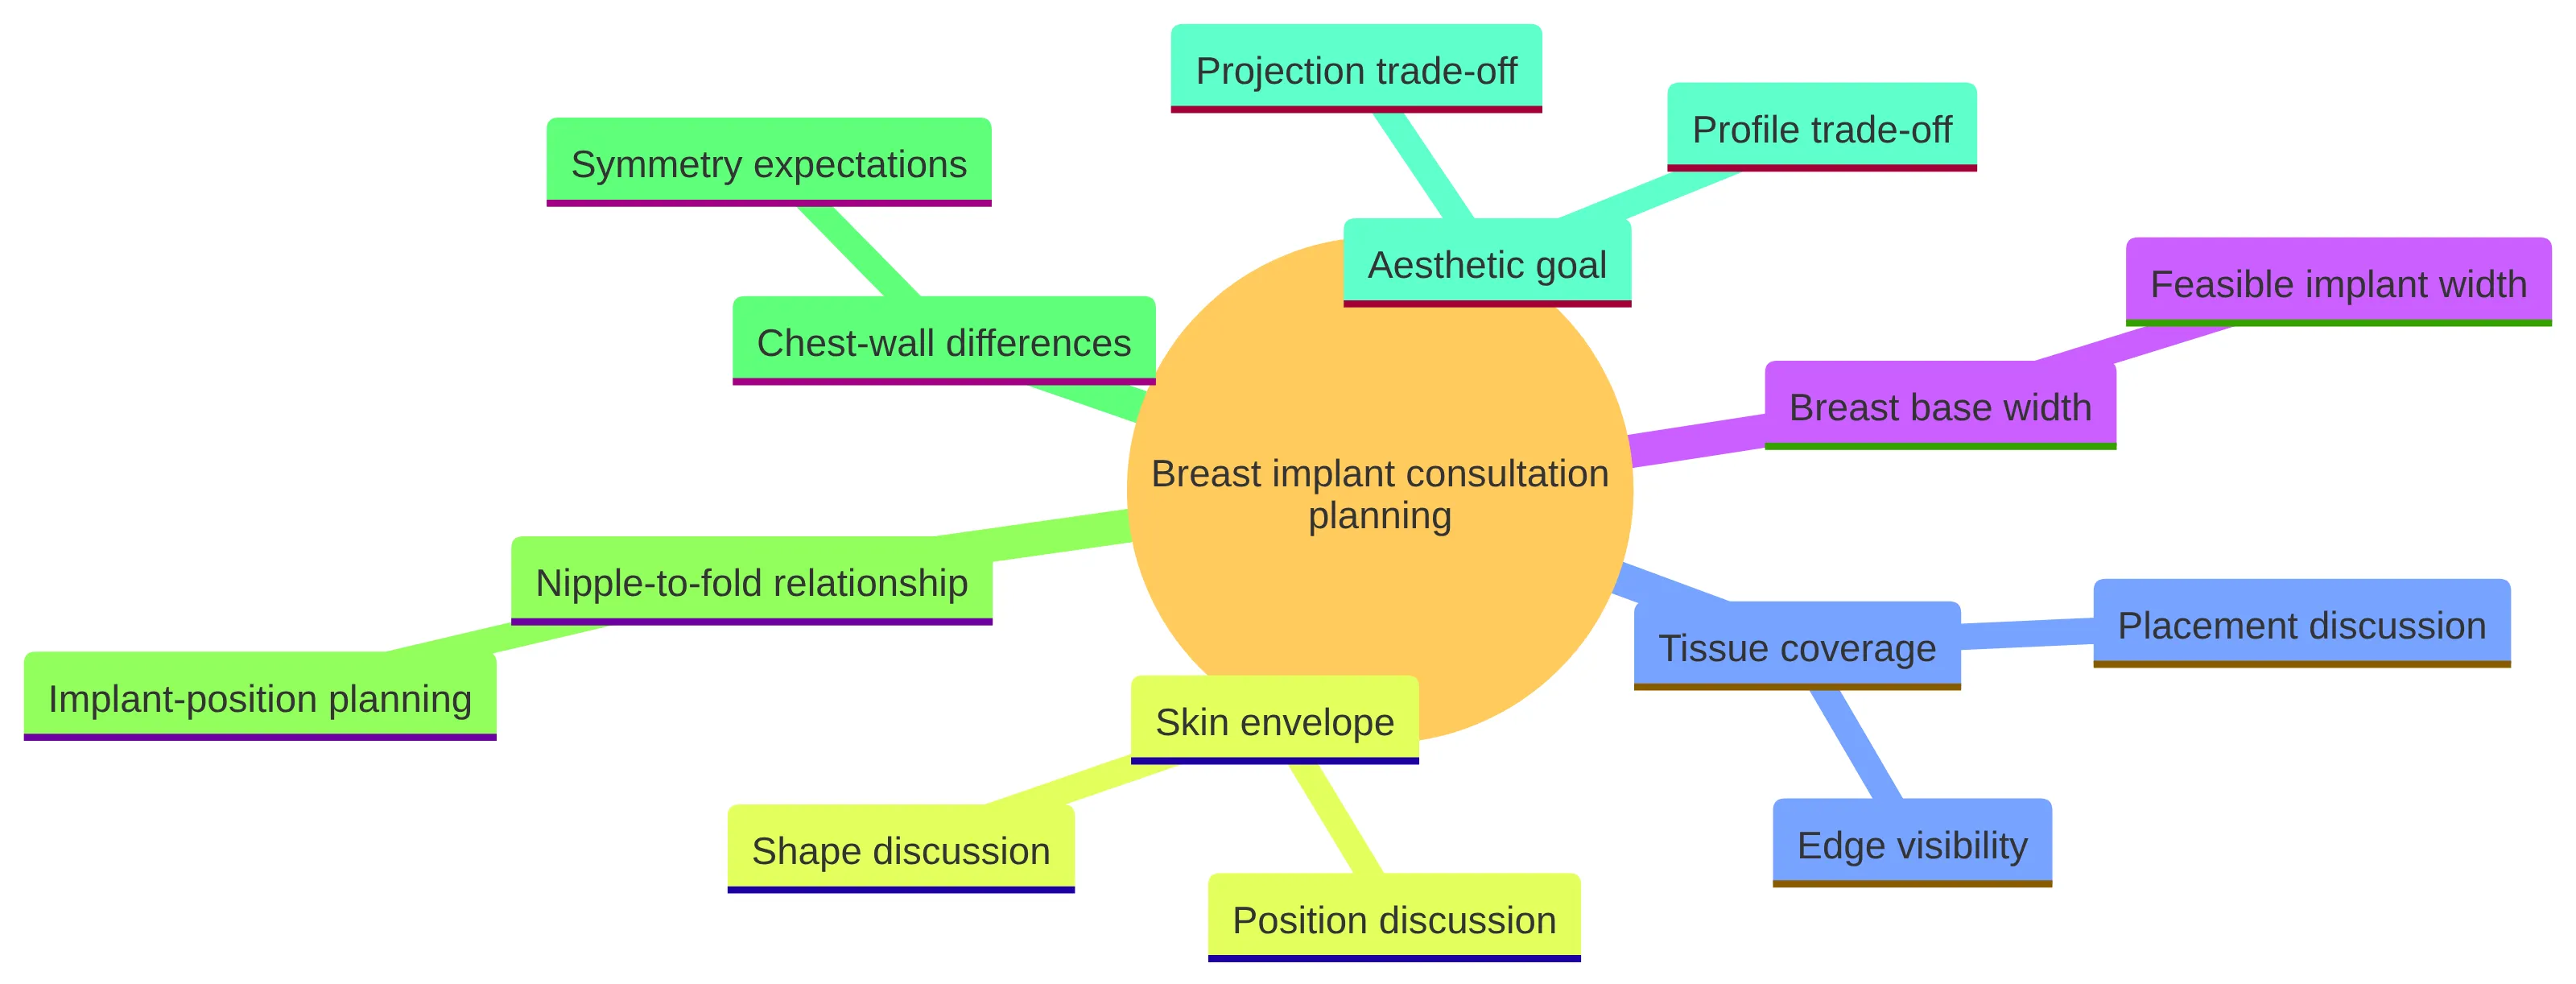
    A mind map showing how breast base width, tissue coverage, skin envelope, nipple-to-fold relationship, chest-wall differences, and the aesthetic goal shape breast implant consultation planning.
    A consultation starts with anatomy, then narrows the discussion to implant width, coverage, position, symmetry, and projection trade-offs.

    A Narrow Breast Base With a Wish for Fullness

    A narrow breast base can make a wish for fullness more specific. The person may be looking for more presence in clothing, greater forward fullness, or an upper-breast change without a broader appearance across the chest. Those are related preferences, but they are not interchangeable descriptions of volume.

    The visible starting point directs attention to the breast footprint: its horizontal width and its relationship to the chest wall. That footprint helps establish which implant widths can be discussed. From there, profile describes forward projection in relation to base width, not volume alone. At a fixed volume, width and projection trade off: spreading volume over a wider base produces less projection, while concentrating it in a narrower base produces more.

    This is why a matching volume number can represent different visual directions. An overly wide implant may extend laterally beyond the natural breast border or make edges more apparent. An implant that is too narrow may not fill the breast base and can leave an under-filled appearance. These are planning trade-offs, not instructions about what any one person should choose.

    In this scenario, the meaningful discussion is not simply whether a larger volume is available. It is whether the desired kind of fullness means more forward projection, a broader footprint, upper-pole emphasis, or some combination of those features. A cup-size target cannot answer that question, because bra sizing does not describe how an implant will sit on an individual frame.

    Visible Asymmetry or Uneven Volume

    When one breast looks different from the other, “uneven volume” may be the first description, but it is not always the complete one. Asymmetry can involve size, shape, position, volume, nipple level, or the chest wall beneath the breasts. Some degree of asymmetry is common and may be a normal variation.

    The visual detail that draws attention can guide the assessment. Unequal fullness in a bra may point the conversation toward volume. One breast sitting differently on the chest, or nipples that do not appear level, brings shape and position into the picture. Assessment may examine breast dimensions, volume, shape, nipple position, chest-wall symmetry, and relevant history because these features can contribute to what is seen.

    Implants alone do not correct nipple asymmetry. Added volume and projection can sometimes make an existing difference more apparent. A source also notes that residual differences may remain noticeable even when objective symmetry improves. The value of naming the visible difference precisely is that it prevents a volume change from being treated as an answer to every part of the asymmetry.

    A plan may address one part of the picture while leaving another relevant. Where skin excess or more significant droop is part of the starting picture, a lift may enter the discussion. The central question is which feature a proposed direction is intended to address, rather than whether asymmetry can be made to disappear.

    Thinner Tissue and a Softer Upper-Pole Preference

    A softer upper-pole preference often starts with an observation about the transition from the chest to the breast. A person may notice little tissue over the upper breast, worry about a sharply defined edge, or prefer less conspicuous upper-pole fullness. That visual priority makes coverage part of the conversation, alongside volume.

    With thinner tissue, visible implant edges, stepping, or rippling may be part of the coverage-and-projection discussion, particularly near the upper and lateral breast. Higher projection can concentrate volume forward, but it does not erase the importance of the tissue overlying it. The same desired volume may therefore be discussed differently for people with different tissue coverage.

    For thin upper-pole tissue, muscle coverage may be discussed as one way to soften transitions and reduce visible edges. Placement does not promise a particular aesthetic result, however. Technique, implant width, and tissue behavior also matter. More coverage does not assure a specific look or remove every trade-off associated with thin tissue.

    Here, the stated preference is a way to clarify what deserves explanation: how tissue coverage, width, projection, and the proposed placement relate to the upper-pole appearance being discussed, along with the limitations of that direction.

    Why Shape, Nipple Level, and Skin Envelope Cannot Be Separated From Volume

    The three starting points overlap at the breast shape, nipple level, and skin envelope. A person seeking fullness may also be noticing a nipple that appears low, lower-pole looseness, or a breast contour that relates differently to the chest wall. These observations do not all describe the same planning issue.

    Nipple level in relation to the inframammary fold is relevant to implant-position planning. Lower-pole skin and soft tissue, the starting nipple-to-fold distance, implant shape and projection, tissue compliance, and fold support can all influence where an implant sits and how the breast takes shape. This is why a visible concern that sounds like “more fullness” may also require attention to breast position and support.

    Skin behavior adds another layer. A tighter envelope and a more compliant envelope do not present the same planning conditions. One study found that postoperative lower-pole stretch materially affected final implant position, supporting discussion of tissue behavior rather than treating the position achieved during surgery as the sole determinant. That finding does not predict an individual outcome.

    An implant and a lift do not answer the same visual concern. An implant discussion addresses added volume and dimensions. A skin or positional concern may require a separate discussion of whether an implant alone is an appropriate tool. When significant droop is present, a pocket strategy is not presented as a reliable substitute for every skin-envelope issue.

    A Plan Includes Its Limits and Longer-Term Questions

    The three scenarios show why a plan needs limits stated alongside its intended purpose. A direction that addresses forward fullness may not resolve a positional concern. A direction that narrows a volume difference may not eliminate nipple asymmetry or chest-wall differences. More coverage may change the discussion of visible edges without assuring a particular upper-pole appearance.

    Recovery belongs in the consultation as a plan-specific conversation. Ask how the proposed direction may affect recovery expectations and what follow-up communication the practice recommends. The appropriate details depend on the proposed surgery and the clinician’s instructions; this article cannot supply an individualized recovery schedule or activity restrictions.

    Longer-term device considerations also belong beside the visible priority that first led someone to consider implants. FDA materials list risks and complications that include breast pain, changes in nipple and breast sensation, additional surgery with or without device removal, capsular contracture, rupture or deflation, BIA-ALCL, systemic symptoms, and possible effects on breastfeeding. The FDA strengthened breast-implant risk-communication requirements in 2021 to support informed decision-making.

    For device-specific complication information and rates, consult the FDA-linked patient labeling for approved implants and discuss the selected device with a qualified clinician. A proposed direction should include its trade-offs, risks, possible future surgery, recovery expectations, and follow-up—not only the appearance concern it is intended to address.

    The Useful Next Step Is a Plan That Fits the Whole Picture

    A narrow base, visible asymmetry, and thinner tissue can all lead someone to ask about breast implants, yet they change the meaning of that question. The common thread is not a universally best volume. It is the need to connect the feature a person sees with the anatomy that may shape the discussion.

    A consultation can use that connection to distinguish forward fullness from width, uneven volume from positional asymmetry, and a softer upper-pole preference from a promise about appearance. Proposed width, profile, projection, coverage, placement, breast shape, nipple level, skin envelope, and chest-wall anatomy all belong to that fuller picture. Schedule a breast augmentation consultation.


    Breast Implant Consultation FAQ

    What should a breast implant consultation focus on besides the volume you want?

    It should connect your goals to breast width, tissue coverage, skin envelope, nipple level, and chest-wall shape. Those factors help set the practical boundaries for what different implant dimensions may or may not do.

    Can implants correct visible asymmetry on their own?

    Not always. Volume differences may be part of the issue, but nipple position, breast shape, skin excess, and chest-wall differences can also matter. In some cases, implants may improve one part of the picture without fully resolving every difference.

    Why does tissue thickness matter when someone wants a softer upper pole?

    Thinner tissue can make edges or rippling more noticeable, so coverage becomes part of the discussion. Placement and implant dimensions may be considered to soften the transition, but no single choice guarantees a specific look.

    How are implant width and profile discussed for a narrow breast base?

    Width should fit the breast footprint first, because width and projection trade off at a given volume.

    What recovery and follow-up questions are worth asking during planning?

    Ask how the proposed plan may affect recovery expectations, what follow-up is recommended, and how the team handles longer-term monitoring. It is also reasonable to review device-related risks and possible future surgery as part of informed decision-making.

  • Breast Augmentation in Beverly Hills: A Decision Path for Volume, Position, and Implant Responsibility

    Breast Augmentation in Beverly Hills: A Decision Path for Volume, Position, and Implant Responsibility

    Start With the Question You Want Surgery to Answer

    Breast augmentation is elective surgery that uses implants or, less commonly, fat transfer to enhance breast size. For many people, the more useful starting point is not “Which implant should I choose?” but “What change am I hoping to see in my proportions, clothing fit, or breast volume?”

    That distinction matters because implant selection is only one part of an individualized treatment plan. A thoughtful discussion connects your goals with your existing breast shape, tissue coverage, skin quality, symmetry, lifestyle, recovery needs, and willingness to manage an implant over time—what would you want surgery to answer for you?

    Natural-looking results can be a planning goal, not a promise. Open discussion of your motivation, expectations, and concerns can help you and a surgeon decide whether surgery is appropriate, while realistic expectations matter because an outcome may not fully match every imagined goal—are you ready to describe both what you hope will change and what you want to preserve?

    If you are also considering facial rejuvenation, body contouring, or med spa care, keep those topics separate from your breast augmentation goals—would separating these priorities make the discussion clearer?

    If surgeon credentials or travel access matter to you, ask directly whether the clinician is a double board-certified plastic surgeon and confirm whether a virtual consultation or Destination Surgery applies to your circumstances—what details would you want verified before scheduling?

    Decision One: Is Added Volume the Change You Want to Evaluate?

    The first decision is whether added volume is the change you want to evaluate. Breast augmentation is designed to add volume, while a lift may be discussed when significant sagging is present because implants alone may not correct that concern—does added volume address the concern you see?

    That distinction cannot be settled by a cup-size goal, a photograph, or general information. An individualized examination is needed to determine whether a lift belongs in the discussion—would you be open to a different approach if it better matched your anatomy?

    Breast revision is a separate consideration for someone with existing implants. It may involve revising, replacing, or removing implants; some cases involve replacement alone, while others require work on soft tissue or breast structure—if you have implants, what change are you trying to evaluate now?

    This first decision is not about choosing a procedure from a list. It is about naming the concern clearly enough to understand whether volume, breast position, or an existing implant result is central—can you state that concern without assuming the answer in advance?

    What Your Starting Anatomy Can and Cannot Answer

    A desired size is useful information, but it cannot determine a surgical plan by itself. During a consultation, you can discuss your goals and concerns, and recommendations may take your medical history and other factors into account—what would make a proposed size feel proportionate to you?

    Bring attention to your starting point: breast width, existing volume, the amount of natural tissue coverage, skin quality, and baseline differences between the breasts. Natural tissue coverage is one consideration when discussing placement, while pre-existing asymmetry may remain after surgery even with careful planning—have you considered which differences you would accept as part of your own anatomy?

    Body proportion and lifestyle also belong in the conversation. For an active patient, exercise and possible muscle interference can be discussion points when considering placement, so your work, training, childcare, and everyday movement are relevant planning details—what activities would you want to protect during recovery and afterward?

    A useful consultation does not promise an identical result to an image or another person’s outcome. Instead, it asks whether your goals, expectations, and motivation align with what surgery can reasonably aim to achieve—can you describe your priorities in terms of balance and proportion rather than a single measurement?

    Decision Two: Weigh Implant Features Only After Defining the Goal

    Once the change being considered is clear, implant features can be considered in context. In the United States, breast implants are FDA-approved devices for augmentation and reconstruction—what information would help you understand the device decision?

    Implants may be saline-filled or silicone-filled, and both have an outer silicone shell. Silicone implants contain cohesive gel, while saline implants are filled with sterile saltwater after placement and may feel firmer; neither option is universally better because anatomy, preferences, and goals matter—what trade-off matters most to you?

    A proposed size, shape, or profile has meaning only in relation to the volume goal and the breast that will support it. Ask for an explanation of how breast width, tissue coverage, body proportion, and desired change informed the recommendation—would the reasoning make sense without relying on a generic ideal?

    Placement, surface, and incision location also belong to the clinical discussion. For someone with little natural breast tissue, submuscular placement may be discussed as a way to help conceal implant edges, but no single feature determines the entire plan—does the proposed approach account for the limits as well as the intended change?

    Decision Three: Consider the Long-Term Device Commitment

    Recovery is not a single standard timetable. Timing varies by procedure, medical history, and other individual factors, so ask how recovery could affect work, childcare, exercise, sleep arrangements, transportation, and the activities that matter in your day-to-day life—who could support you while you recover?

    Implants are not lifetime devices, and future surgery to replace one or both implants may be needed. Pregnancy, weight loss, and menopause may also influence the appearance of augmented breasts over time, which is why the decision is about more than the immediate surgical result—are you comfortable considering the longer arc of this choice?

    For silicone implants, discuss the current FDA-recommended MRI or ultrasound screening schedule with a qualified clinician: five to six years after placement and every two to three years thereafter. Routine screening can assess implant integrity and identify rupture or silicone leakage, and rupture may be asymptomatic for some women—have you included future screening in your planning?

    This is general educational information, not a personal monitoring plan. Ask the clinician who knows your health history and implant details how follow-up, routine breast health care, and implant screening should fit together—do you know which follow-up questions you would want answered before proceeding?

    A practical way to assess the long-term commitment is to separate three responsibilities: keeping scheduled follow-up discussions, maintaining routine breast health care, and understanding when implant screening may be relevant. This does not mean every future change requires surgery, but it does mean the initial decision should leave room for future evaluation if your priorities, breast appearance, or implant condition changes—would you be prepared to revisit the plan if circumstances change over time?

    Monitoring is different from waiting until you notice a problem. Because rupture may be asymptomatic for some women, follow-up discussions can help you understand how implant integrity may be evaluated even when you do not notice a change; for silicone implants, ask who will help you keep track of the current FDA-recommended imaging schedule—would you be able to keep that information accessible over time?

    It can also help to regard a future implant discussion as an evaluation rather than a predetermined outcome. A later conversation may be relevant after a complication, a change in breast appearance, or a change in your own priorities, and the appropriate next step depends on the reason and an individualized assessment—does this longer perspective fit your expectations for an elective device decision?

    Understand the Uncertainty That Remains With Any Plan

    A plan can be carefully individualized and still involve uncertainty. Potential surgical and implant-related complications include anesthesia-related risks, bleeding, infection, fluid collections, hematoma, sensation changes, capsular contracture, leakage or rupture, implant malposition, persistent pain, poor scarring, and possible revision surgery—what uncertainties would be most important for you to understand?

    BIA-ALCL is a type of T-cell lymphoma that can develop following breast implants. FDA materials state that it appears more often in patients with textured implants, making the surface of a proposed device an important topic for a current discussion—would you want to understand the safety information for the device being considered?

    Breast implants and breast surgery may interfere with successful breastfeeding. Sensation changes may be temporary or permanent and may affect sexual response or nursing, while implants can interfere with mammography and breast exams; patients should tell their mammography technician about implants—how do these considerations relate to your present or future priorities?

    Implant removal can also change breast appearance, including size or shape, dimpling, puckering, sagging, chest-wall concavity, or incision appearance. These possibilities do not predict an individual outcome, but they show why the device decision includes more than the initial operation—does knowing the range of future possibilities change how you view the decision?

    Baseline asymmetry may remain after surgery, and implant displacement can contribute to asymmetry or other cosmetic concerns. A proposed plan cannot erase every variable, so realistic expectations should include what may remain outside a surgeon’s control—can you distinguish a planning goal from an assured appearance?

    Use the Three Decisions to Decide Whether to Continue

    Write down questions before your consultation. The answers may help you clarify or refine your goals, especially when you feel pulled between a desired look, practical recovery needs, and uncertainty about future surgery—what do you need to understand to make an unhurried decision?

    Use this list to connect the proposed plan to your priorities:

    • What are your qualifications in plastic surgery, and where would the procedure be performed?
    • What about my breast anatomy, tissue coverage, skin quality, asymmetry, and body proportion supports this recommendation?
    • Why are you recommending this implant fill, size, shape, profile, surface, incision, and placement for me?
    • What realistic expectations should I have, including differences that may remain after surgery?
    • How might recovery affect work, childcare, exercise, and other usual responsibilities?
    • What are the important risks in my situation, and how are complications handled?
    • How could surgery affect breastfeeding, nipple or breast sensation, mammography, and routine breast care?
    • What follow-up and silicone-implant screening discussions should I plan for?
    • What future surgeries might become relevant, and what are my options if I am dissatisfied?

    A surgeon should be able to explain the reasoning behind a recommendation in language you understand. If an answer does not connect the plan to your stated goals and practical circumstances, ask for clarification before deciding—can you repeat back the plan and why it was chosen?

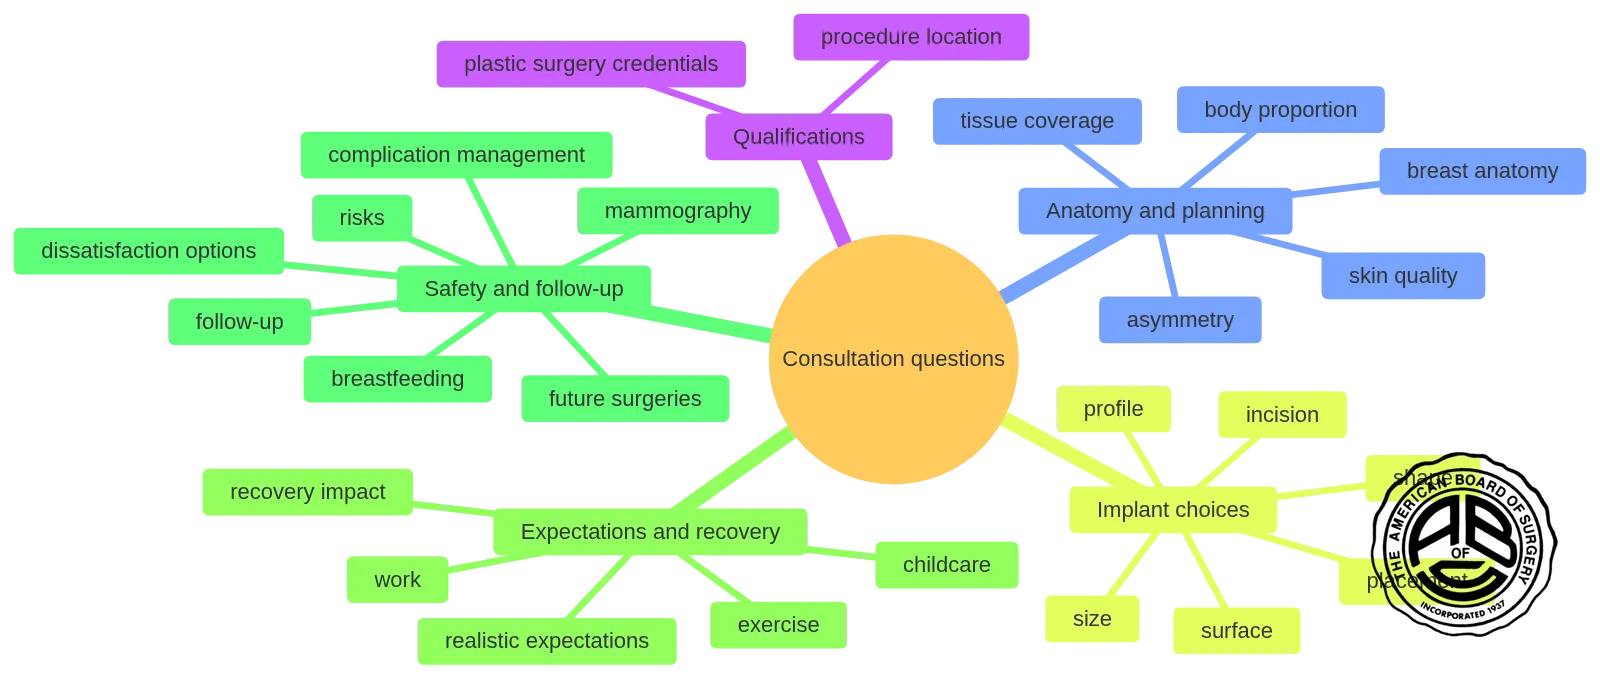
    A mind map of consultation questions covering qualifications, anatomy and planning, implant choices, expectations and recovery, and safety and follow-up.
    A consultation should connect each recommendation to your anatomy, goals, recovery needs, and long-term planning.

    Make the Next Decision With Context

    General guidance can help you organize questions, but it cannot determine candidacy or select an implant, placement, lift, or breast revision for you. Those decisions require an individualized discussion of your goals, health history, anatomy, realistic expectations, recovery responsibilities, and comfort with long-term device considerations—are you ready to have that conversation with the full context in view?

    If you are considering this procedure in Beverly Hills, bring your priorities, questions, and concerns to a consultation with Dr. Golshani. If a virtual consultation would be more practical, confirm directly whether it is available and appropriate for your situation—would a focused first discussion help you decide whether to move forward?


    Frequently Asked Questions About Breast Augmentation Planning

    What is breast augmentation intended to change?

    It is surgery used to add breast volume, usually with implants and less often with fat transfer. The goal is typically a change in size and proportion, not a promise of a specific look.

    How do implant size, shape, and placement get chosen?

    Those choices are individualized to your breast width, tissue coverage, skin quality, asymmetry, body proportion, and lifestyle. Your surgeon should explain why a particular combination is being suggested for you.

    What should I ask about recovery before deciding on surgery?

    Ask how recovery may affect work, childcare, exercise, sleep, and daily support needs. Recovery timing varies by procedure and by patient, so it helps to plan around your real schedule instead of a generic timeline.

    What long-term issues should I understand before getting implants?

    Implants are not lifetime devices, and future surgery may be needed. You should also understand routine monitoring, possible implant rupture or leakage, changes in sensation, breastfeeding impact, and the chance that revision surgery could become relevant later.

    What questions should I bring to a breast augmentation consultation?

    Ask about qualifications, the proposed surgical plan, realistic expectations, risks, complication management, follow-up, and how the plan fits your anatomy and goals. Good answers should connect each recommendation to a clear reason.